Bhagyashree Tirpude1, Nitya Malladi2, Khyati Jain3, Manisha Madkaikar4.
1Department of Pediatrics, Government Medical College, Bhandara, Maharashtra, India,
2Department of Dermatology, KEM Hospital, Mumbai, India,
3Seth G S Medical College, KEM Hospital, Mumbai, India,
4Department of Paediatric Immunology and Leukocyte Biology, National Institute of ImmunoHematology, KEM Hospital, Mumbai, India.
ADDRESS FOR CORRESPONDENCE
Bhagyashree Tirpude, Department of Pediatrics, Government Medical College, Bhandara, Maharashtra, India.
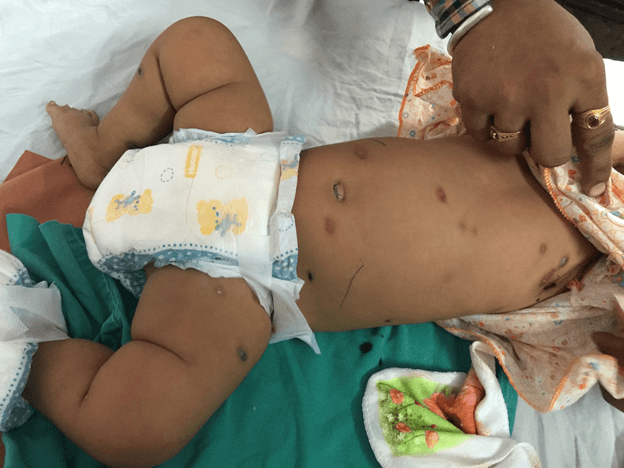
Email: bhagyashree.tirpude2@gmail.com | | Abstract | | A 7 months old female child received BCG vaccine on day 2 of life and developed left axillary adenopathy on Day 15 of life which grew pseudomonas aeruginosa which responded to antibiotics. At 3 months of age she was diagnosed to have hemophagocytic lymphohistiocytosis (HLH) along with cytomegalovirus (CMV) infection which was treated with steroids, cyclosporine and ganciclovir. At 5 months of age she again had left axillary adenopathy that showed acid fast bacilli (AFB) on smear. She also had hepatosplenomegaly and thus disseminated BCGosis was suspected. She was detected to have partial dominant interferon gamma receptor 1 defect. After one month of anti-tuberculous therapy (ATT), she developed erythematous papules and nodules all over the body suggestive of cutaneous TB. She was continued on same ATT which was given for a year. | | | | Keywords | | BCG vaccine, Disseminated BCGiosis, Mycobacterial Disease, MSMD. | | | | Introduction | | Bacille Calmette-Guerin (BCG), a live attenuated vaccine is routinely given to neonates in settings where tuberculosis (TB) is endemic.1 Immunodeficient individuals are at high risk of developing BCG related complications like regional adenopathy i.e. BCG-itis or disseminated disease i.e. BCG-osis.2,3,4 Mendelian susceptibility to mycobacterial diseases (MSMD) are a diverse group of hereditary disorders leading to impaired immune response that creates high susceptibility to mycobacterial infections. Mycobacterium tuberculosis (MTB), BCG and non-tuberculous mycobacterium (NTM) may cause a severe disease in such patients.5 We report an infant with partial interferon gamma receptor 1 (partial IFN-γ R) defect who had BCG-osis involving left axillary node, liver, spleen and skin. | | | | Case Report | A 7 months old female child born at full-term to parents of non-consanguineous marriage was referred to us for further management of her TB. She was born at full term and had a birth weight of 3.5 kg. She received BCG vaccine on day 2 of life. After 2 weeks, she developed left axillary lymphadenopathy which formed an abscess for which incision and drainage done. Pus culture grew pseudomonas aeruginosa for which antibiotics was given. At 3 months of age, she was admitted to another hospital with fever, anasarca, petechial rash, pallor and hepatosplenomegaly. Investigations revealed anemia (Hemoglobin = 6.7 gm%), leucocytosis (white cell count 43,800/cumm with 37% polymorphs, 48% lymphocytes and 7% monocytes), thrombocytopenia (platelet count 34,000/cumm/dl), hyperbilirubinemia, (direct bilirubin -1.7 mg/dl) and ultrasound (USG) showed hepatic and splenic microabscesses. Cytomegalovirus (CMV) IgM was positive. She had high serum ferritin (6304 ng/ml), high triglycerides (479 mg/dl), low serum fibrinogen (96 mg/dl) and bone marrow examination revealed hemophagocytes. Serum perforin levels were 12%. Immunodeficiency work up in form of nitroblue tetrazolium (NBT) test (98%), serum IgG [2095 mg/dl (Normal 840-1700)], IgM [245 mg/dl (normal-35-220)], IgA [71 mg/dl (Normal-0-83)], CD3 (71%), CD4 (25%) was normal. She was diagnosed to have hemophagocytic lymphohistiocytosis (HLH) along with CMV and treated with IV dexamethasone, cyclosporine, ganciclovir and cotrimoxazole and fluconazole prophylaxis for a period of 1 month. The infant was readmitted at 6 months of age with complaints of fever and maculopapular rash and a discharging sinus in the left axilla. Her weight at the time of admission was 6kg. Pus sent for smear, showed acid fast bacilli (AFB). She was referred to our hospital for further management. On presentation to us, her weight was 5.9 kg. She had discharging left axillary lymph node and hepatosplenomegaly. Disseminated BCGiosis was suspected. Four drug anti tuberculous treatment (ATT) consisting of isoniazid (H), rifampicin (R), ethambutol (E) and ofloxacin (Ofx) were started. Serum ferritin fibrinogen and triglycerides were normal. In view of clinical suspicion of MSMD, she was investigated and detected to have partial dominant interferon gamma receptor 1 defect. Fifteen days after starting ATT, she had bulging anterior fontanelle. Cerebrospinal fluid (CSF) and USG skull were normal. CSF TB-culture and Xpert/Rifa test were negative. Pseudotumour cerebri was suspected and ofloxacin was stopped to which she responded. After one month of ATT, she developed erythematous papules and nodules all over the body. (Figure 1) A few lesions were associated with blood tinged discharge. Skin biopsy revealed suppurative granulomatous inflammation consisting of histiocytes, neutrophils and few giant cells suggestive of cutaneous TB. She was continued on same ATT. After 3 months of ATT, skin lesions were healing and the discharge had stopped. Her ATT was stopped after 1 year. She is on regular follow up and doing well.
Figure 1. Cutaneous TB in a child with disseminated TB.
 | | | | Discussion | BCG vaccine is generally safe, however, possible complications including hypersensitivity, localized lymphadenitis, fistula formation and rarely disseminated disease and death may occur. Disseminated disease is the most serious complication that may develop in children with immunodeficiency disorders. The commonly associated immunodeficiencies include severe combined immunodeficiency, cellular immune defects and chronic granulomatous disease.6,7 There are a few reports of disseminated BCG infection in normal hosts.8,9,10 In addition, recently it has been shown that patients with inherited deficiency of IL12/IL23IFNγ axis show increased susceptibility to invasive diseases caused by the intra-macrophage pathogens such as salmonella and mycobacteria.11 IL-12/IL-23/IFN-γ axis consists of two complementary components, first an IL-12/IL-23 component and second an IFN-γ component. Mycobacterial disease occurred in 77% cases with IL-12/IL-23 component deficiency and in 94% cases with IFN-γ component deficiency.12 Predisposition to mycobacterium is called mendelian susceptibility to poorly virulent mycobacteria such as BCG and NTM. It is thought to be due to impaired immunity, specifically altering host defences against mycobacteria. This syndrome is characterized by parental consanguinity, familial forms and an autosomal recessive pattern of inheritance. The rarity and heterogeneity of the syndrome make the diagnosis difficult. Different types of mutation have been detected in four genes (IFNGRI, IFNGR2, IL12B, IL12RB1) resulting in eight different disorders whose common pathogenic mechanism is impaired IFN-γ mediated immunity. Severity of the clinical phenotype depends on the genotype. Complete IL-12 40, IL-12RB1 IL-12RB1 deficiency and partial IFN-γ R1 and IFN-γ R2 deficiencies generally lead to curable infections with antibiotics supplemented with IFN-γ. Complete IFN-γ R1 and IFN-γ R2 deficiencies predispose to overwhelming infections in early childhood which respond poorly to antibiotics and are ineffective to IFN-γ treatment.5 Bone marrow transplantation gives a possible hope while gene therapy is the treatment of choice. Our partial IFN-γ R defect with disseminated BCGiosis and a previous HLH and CMV infection. Though she had severe diseases, all of them were controlled and treated with medications. She is currently on regular follow up and is currently asymptomatic.
In families who have already had a severely affected child, genetic counselling with the possibility of carrier detection and prenatal diagnosis can be offered. | | | | Compliance with Ethical Standards | | Funding None | | | | Conflict of Interest None | | |
- Guani-Guerra E, Reyes L, Oswaldo S, Guerra R, Manuel J, et al. A male infant with recurrent opportunistic infections and fulminant BCG-osis. Rev Inst Nal Enf Resp Mex 2008;21:(2):123-126.
- Bustamante J, Aksu G, Vogt G, de Beaucoudrey L, Genel F, Chapgier A. BCG-osis and tuberculosis in a child with chronic granulonatous disease. J Allergy clin Immunol. 2007 Jul;120(1):32-8. [CrossRef] [PubMed]
- Shurin MR, Smolkin YS. Immune- Mediated Diseases from Theory to Therapy. Springer. New York 2007:75-81. [CrossRef] [PubMed]
- Sadeghi-Shabestari M, Rezaei N. Disseminated bacilli calmette-Guerin in Iranian Children with severe combined immune deficiency. Int J Infect Dis. 2009 Nov;13(6):e420-3. [CrossRef] [PubMed]
- Casanova JL. Mendelian susceptibility to mycobacterial disease. Orphanet Encyclopedia September 2003. Available at URL: https://www.orpha.net/data/patho/GB/uk-bcgite.pdf. Accessed on 11th June 2016.
- Paiman SA, Siadati A, Mamishi S, Tabatabaie P, Khotaee G. Disseminated Mycobacterium bovis infection after BCG vaccination. Iran J Allergy Asthma Immunology. 2006; 5(3): 133- 137.
- Talbot EA, Perkins MD, Silva SF, Frothingham R. Disseminated bacilli Calmette-Guerin disease after vaccination: case report and review. Clin Infect Dis. 1997; 24: 1139-1146. [CrossRef] [PubMed]
- Doffinger R, Dupuis S, Picard C, Fieschi C, Feinberg J, Barcenas-Morales G, et al. Inherited disorders of IL-12- and IFN gamma-mediated immunity: a molecular genetics update. Mol Immunol. 2002; 38: 903-909. [CrossRef] [PubMed]
- Gonzalez B, Moreno S, Burdach R, Valenzuela MT, Henriquez A, Ramos MI, et al. Clinical presentation of Bacillus Calmette-Guerin infections in patients with immunodeficiency syndromes. Pediatr Infect Dis J. 1989; 8(4): 201- 06.
- Katzir Z, Okon E, Ludmirski A. Generalized Lymphadenitis following BCG vaccination in an immunocompetent 12 years old boy. Eur J Pediatr. 1984; 141(3): 165-170. [CrossRef] [PubMed]
- Mohapatra S, Sethy S, Mohanty P, Mohapatra A, Pradhan S. Primary paediatric TH1 immunodeficiency with BCG-osis. Int J Case Reports Images. 2012; 3(5): 36-40. [CrossRef]
- Hesseling AC, Rabie H, Marais BJ, Manders M, Lips M, Schaaf HS, et al. Bacille Calmette Guerin vaccine-induced disease in HIV-infected and HIV-uninfected children. Clin infect Dis 2006 Feb 15;42(4):548-8. [CrossRef] [PubMed]
|
| Cite this article as: | | Tirpude B, Malladi N, Jain K, Madkaikar M. Disseminated BCGiosis with cutaneous involvement in a child with Mendelian Susceptibility to Mycobacterial Diseases (MSMD). Infection Child J. 2026;1. |
|